
Category: Women’s Health

  • PCOS Diet and Supplements: A Science-Based Guide to Managing Symptoms Naturally

    PCOS Diet and Supplements: A Science-Based Guide to Managing Symptoms Naturally

    What Is PCOS and Why Does It Matter?

    Polycystic ovary syndrome (PCOS) is the most common endocrine disorder in women of reproductive age, affecting an estimated 8 to 13 percent of women worldwide according to the World Health Organization. Many of those affected remain undiagnosed. PCOS shows up as irregular or absent periods, elevated androgen hormones (linked to acne, excess hair growth, and hair thinning), and frequently, polycystic-appearing ovaries on ultrasound.

    PCOS is far more than a fertility issue. It is a lifelong metabolic condition closely tied to insulin resistance, weight gain, type 2 diabetes risk, and cardiovascular health. The encouraging news: research consistently shows that targeted nutrition, movement, and a small number of well-studied supplements can meaningfully improve symptoms, hormones, and metabolic markers, often alongside medical treatment.

    How PCOS is diagnosed

    Doctors use the Rotterdam criteria, which require two of the following three findings after excluding other causes: irregular or absent ovulation, clinical or biochemical signs of high androgens, and polycystic ovarian morphology on ultrasound. More recent international guidelines emphasize that PCOS is a diagnosis of exclusion, which is why a proper workup matters.

    The Insulin Connection: The Engine Behind Most PCOS Symptoms

    Here is the most important concept in PCOS: studies suggest that between 50 and 70 percent of women with PCOS have insulin resistance, regardless of body weight. When cells stop responding well to insulin, the pancreas compensates by releasing more of it. Chronically high insulin then acts directly on the ovaries and adrenal glands, telling them to produce extra testosterone. High insulin also suppresses the liver’s production of sex hormone-binding globulin (SHBG), leaving more testosterone free and active in circulation.

    This is why a low-carb crash diet is not the answer, but stabilizing insulin almost always is. Every strategy below targets this loop from a different angle.

    The Evidence-Based PCOS Diet

    1. Lower the glycemic load of your meals

    Glycemic load is a measure of how sharply a food raises blood glucose. Diets with a lower glycemic load improve insulin sensitivity and androgen levels in women with PCOS, according to multiple randomized trials. Practical ways to lower glycemic load without counting every gram:

    • Build meals around protein first (eggs, fish, poultry, legumes, Greek yogurt), then vegetables, then starches.
    • Swap refined starches (white bread, rice cakes, most cereals) for lentils, quinoa, steel-cut oats, and sweet potato in moderation.
    • Pair any carbohydrate with protein, fat, or fiber to blunt the glucose response.
    • Keep sweets and sugary drinks as occasional, deliberate choices rather than daily habits.

    2. Prioritize protein and fiber at every meal

    Higher protein intake increases satiety, preserves lean mass, and indirectly lowers insulin demand. A practical target for many women with PCOS is roughly 1.5 grams of protein per kilogram of body weight daily, adjusted with a dietitian. Fiber, meanwhile, slows glucose absorption and feeds the gut bacteria that support estrogen clearance, a point explored in depth in our guide to estrogen dominance signs, causes, and natural solutions, which overlaps heavily with PCOS hormone patterns.

  • 3. Eat an anti-inflammatory, Mediterranean-style pattern

    PCOS is associated with low-grade chronic inflammation. Mediterranean-style eating, rich in olive oil, fatty fish, vegetables, legumes, and nuts, has consistently positive effects on insulin sensitivity and inflammatory markers in controlled studies, and trials applying this pattern to PCOS report improvements in cycle regularity and androgen levels. Our science-based hormone balance eating plan is built on the same principles.

    4. Omega-3s deserve a place on the plate

    Several randomized trials in women with PCOS found that omega-3 supplementation improved insulin sensitivity, triglycerides, and testosterone levels. Fatty fish twice weekly is the dietary foundation; supplements make sense when intake falls short, which is why fatty fish and quality omega-3 intake deserve a permanent place in the diet.

    5. Watch the thyroid, too

    Autoimmune thyroid disease travels with PCOS more often than chance would predict, and an underactive thyroid worsens fatigue, weight struggles, and cycle problems. If you carry extra weight despite doing things right, testing TSH is worthwhile; our article on thyroid and weight gain explains the hidden connection.

    Supplements with Real Evidence in PCOS

    Myo-inositol: the best-studied PCOS supplement

    Inositol is a sugar-like molecule involved in insulin signaling. Meta-analyses of randomized trials have repeatedly found that myo-inositol improves insulin sensitivity, testosterone levels, and cycle regularity in women with PCOS. Doses of 2 to 4 grams daily are common, and some trials and reviews favor a 40:1 ratio of myo-inositol to D-chiro-inositol, mirroring the body’s natural ratio. Results typically appear over 8 to 12 weeks.

    Vitamin D

    Between 60 and 80 percent of women with PCOS have insufficient vitamin D, and low levels correlate with more severe insulin resistance. Trials of vitamin D supplementation show small improvements in insulin markers, cycles, and androgen levels, with the clearest benefits in women who start deficient. You can read about the broader hormonal importance in our article on vitamin D and hormone health.

    Berberine

    Berberine, a plant compound that improves insulin sensitivity, has shown improvements in insulin, lipid, and cycle markers in PCOS trials, comparable in some studies to metformin. It deserves its own full review, which we will cover separately on this site.

    Other options with early evidence

    N-acetylcysteine (NAC) and chromium have trial evidence for insulin sensitivity in PCOS, though the data is smaller. DIM, a compound from cruciferous vegetables, may help some women with estrogen metabolism patterns common in PCOS; see our piece on DIM supplements for women’s hormone balance.

    Lifestyle Factors That Multiply Diet Results

    • Resistance training: muscle is the body’s biggest glucose sink. Two to three strength sessions weekly improve insulin sensitivity even without weight change.
    • Even modest weight loss: trials show losing just 5 to 10 percent of body weight restores ovulation and cycles in a meaningful share of overweight women with PCOS.
    • Sleep: poor sleep worsens insulin resistance; aim for 7 to 9 hours. and evidence-based options like magnesium glycinate can help consistency.
    • Chronic stress: cortisol antagonizes reproductive hormones; evidence-based stress-management strategies apply directly to PCOS.

    When to See a Doctor

    See a gynecologist or endocrinologist if you suspect PCOS: irregular cycles, androgen symptoms, or unexplained weight resistance deserve a proper workup including hormone panels, an oral glucose tolerance test, and thyroid evaluation. Supplement and diet strategies work best alongside, not instead of, medical care. Metformin, combined oral contraceptives, letrozole for fertility, and newer insulin-sensitizing options all have a role depending on goals.

    What a PCOS-Friendly Day of Eating Looks Like

    Principles help, but a concrete example makes them real. Here is a day built around the evidence summarized above:

    • Breakfast: a three-egg omelet with spinach, tomato, and feta, plus half an avocado. Leading with protein blunts the glucose spike that a cereal-based breakfast would cause.
    • Lunch: a large salad with grilled chicken or chickpeas, olive oil dressing, pumpkin seeds, and a small portion of quinoa.
    • Snack: plain Greek yogurt with berries and cinnamon, or a small handful of walnuts with an apple.
    • Dinner: baked salmon with roasted broccoli and a modest serving of sweet potato, finished with olive oil and lemon.
    • Optional evening drink: chamomile or mint tea instead of sweetened drinks, which matter more for insulin than most people expect.

    Notice the pattern: every meal anchors protein and fiber first, carbohydrates ride along in controlled portions, and healthy fats keep the glycemic load low while supporting hormone production. There is no demonized food group.

    Things Worth Reducing (Not Because of dogma, But Because of Insulin)

    • Liquid sugar: sodas, sweetened coffees, and juices deliver large glucose loads in minutes with zero satiety.
    • Ultra-processed snack foods: refined starch plus seed oil combinations drive the insulin spikes and crashes that intensify PCOS cravings, which are often genuine, physiology-driven hunger.
    • Skipping meals and late-night grazing: both promote blood sugar swings and can raise evening cortisol, working against every hormone goal. Regular protein-anchored meals are genuinely therapeutic in this condition.
    • Excessive caffeine on an empty stomach: caffeine itself is fine for most, but the accompanying cortisol spike hits harder when unaccompanied by food.

    PCOS and Long-Term Health: The Bigger Why

    The most important sentence in this guide: managing insulin in PCOS is not just about cycles and skin. Women with PCOS carry several-fold higher lifetime risks of type 2 diabetes, gestational diabetes, nonalcoholic fatty liver disease, and cardiovascular disease. The International PCOS Guideline emphasizes that diagnosis and management should begin early and should include metabolic assessment, not only reproductive care. Every one of the nutrition and lifestyle levers described above works on that longer timeline, which is why consistency beats intensity.

    The Bottom Line

    PCOS responds well to a systematic approach: stabilize insulin through smart meal structure and Mediterranean-style eating, add myo-inositol and correct any vitamin D shortfall, train for muscle, protect sleep, and manage stress. None of these is a cure on its own, but together they address the root metabolic drivers that make PCOS worse, and that is where the research says the real progress happens.

    This article is for informational purposes only and is not medical advice. Always consult a qualified healthcare provider before making changes to your diet, supplements, or treatment plan.

  • Thyroid and Weight Gain: The Hidden Connection Explained by Science

    Thyroid and Weight Gain: The Hidden Connection Explained by Science

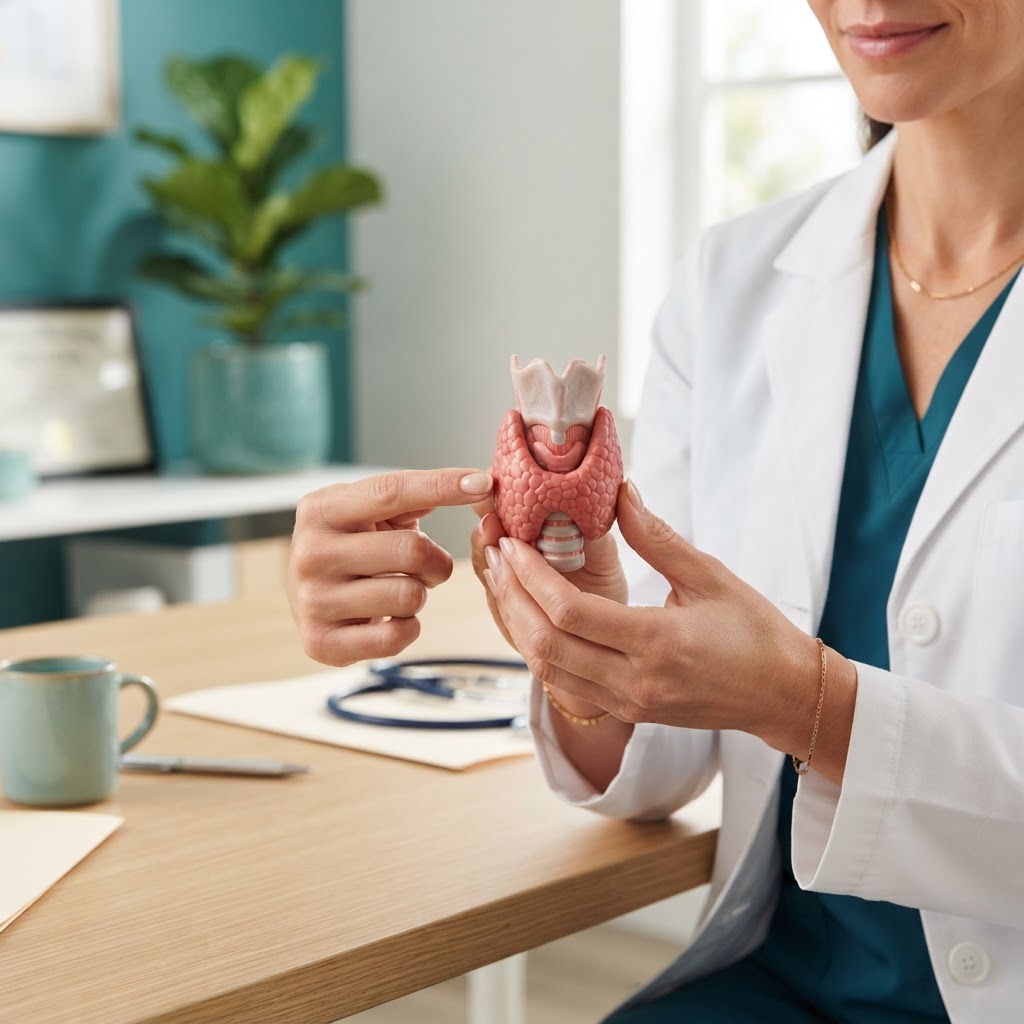
    Unexplained weight gain, fatigue, and feeling cold all the time: for millions of people, especially women over 40, these symptoms trace back to one small butterfly-shaped gland. The thyroid controls your metabolic rate, and when it slows down, everything slows down with it. This guide explains the connection between thyroid function and weight, and what actually helps.

    What the Thyroid Actually Does

    The thyroid produces T4 and T3, hormones that tell every cell in your body how fast to burn energy. When production drops (hypothyroidism), your basal metabolic rate falls, often by 5 to 15 percent. You burn fewer calories at rest, feel colder, tire more easily, and retain water. Much of the early “weight gain” in hypothyroidism is actually fluid retention, but the metabolic slowdown is real.

    Signs Your Thyroid May Be Slowing You Down

    The classic symptoms are fatigue, cold intolerance, dry skin, hair thinning, constipation, brain fog, low mood, and unexplained weight gain. Symptoms are often dismissed as stress or normal aging. Women are five to eight times more likely than men to develop thyroid problems, and risk rises sharply around perimenopause (read our perimenopause nutrition guide), when estrogen shifts can interact with thyroid function. If symptoms overlap with cycle changes, also review our guide to estrogen dominance (estrogen dominance signs and solutions).

    Why Thyroid Problems Make Weight Loss Harder

    Three mechanisms stand out. First, a lower metabolic rate means your maintenance calories drop, so the same diet that once maintained your weight now gains weight. Second, fatigue reduces spontaneous movement and training intensity, shrinking total daily burn. Third, chronic stress and thyroid issues feed each other: elevated cortisol (how to lower cortisol naturally) suppresses the conversion of T4 into the active T3 your cells need.

    Testing: Ask for the Full Panel

    Many doctors test only TSH, the pituitary signal. Ask for TSH, free T4, free T3, and thyroid antibodies (TPO and TG). Antibodies point to Hashimoto’s, the autoimmune cause behind most hypothyroidism in developed countries. Subclinical patterns, where TSH is mildly elevated but T4 is normal, are common and worth monitoring, especially with symptoms.

    Nutrients That Support Thyroid Function

    The thyroid needs specific raw materials: iodine to build hormones, selenium to convert T4 to T3, zinc for that same conversion, and iron to carry hormones into cells. Brazil nuts, eggs, fish, and pumpkin seeds cover most needs. Do not mega-dose iodine without testing, because excess iodine can worsen autoimmune thyroid disease. If you supplement zinc, see our guide on zinc and hormone health (zinc and hormone health).

    Lifestyle Levers That Matter

    Prioritize sleep (7-9 hours, since poor sleep raises cortisol and lowers T3), strength training to preserve metabolic muscle mass, and stress management. Aim for steady blood sugar rather than extreme dieting: very low calorie diets further suppress T3 and can backfire. Adequate protein matters too, especially after 40 (our protein guide for women over 40).

    When to See a Doctor

    If you have two or more symptoms listed here, request a full thyroid panel. If you are already on thyroid medication, take it on an empty stomach, away from coffee, calcium, and iron, and retest 6-8 weeks after any dose change.

    The Bottom Line

    Thyroid dysfunction is common, under-tested, and a legitimate metabolic reason weight loss feels impossible. Test properly, correct nutrient gaps, manage stress, and work with your doctor on treatment if labs confirm it. The scale usually responds once the gland is properly supported.

  • Protein and Strength Training After 40: A Practical Guide for Women in Perimenopause and Beyond

    Protein and Strength Training After 40: A Practical Guide for Women in Perimenopause and Beyond

    Changes in body composition, energy, and recovery are common in midlife, but losing strength is not an inevitable part of menopause. A practical combination of progressive resistance exercise, adequate food, and enough protein can support muscle and function through perimenopause and later life. Protein is not a hormone treatment, and no single food reverses menopause. It is, however, one useful building block alongside movement, sleep, and appropriate medical care.

    This guide explains what the evidence can and cannot say, how to build a sustainable strength routine, and how to estimate protein needs without turning meals into a math problem. For a broader food-first approach, see our perimenopause nutrition plan and our overview of menopause-related hormone symptoms and when to seek care.

    Why muscle deserves attention in midlife

    Skeletal muscle helps with everyday tasks such as carrying groceries, climbing stairs, and getting up from a chair. It also contributes to glucose use and physical resilience. Aging, inactivity, illness, and inadequate nutrition can all contribute to declining muscle strength or mass. Menopause may coincide with changes in fat distribution and body composition, but the timing and degree vary widely. It is inaccurate to attribute every midlife change to estrogen alone.

    Resistance training provides a direct stimulus for muscle and strength. The goal is not to chase a particular body shape or to “fix” a normal transition. It is to keep doing the activities that matter to you, reduce the chance that ordinary tasks become difficult, and build capacity for the future. Exercise can also support bone health, balance, and cardiometabolic health, though individual results differ.

    How much protein do women over 40 need?

    The adult Recommended Dietary Allowance is 0.8 grams of protein per kilogram of body weight per day, a level designed to cover the needs of most healthy adults. Some expert groups recommend higher intakes for older adults, particularly during illness or recovery. The PROT-AGE Study Group proposed 1.0–1.2 g/kg/day for many healthy older adults, while emphasizing individual health status and activity. These are not menopause-specific prescriptions, and higher is not automatically better.

    For a healthy, active adult, a reasonable discussion with a clinician or registered dietitian may include a range around 1.0–1.2 g/kg/day, especially when strength training or aiming to preserve muscle during weight loss. People with chronic kidney disease or other conditions affecting protein handling should not adopt a high-protein target without medical guidance. Body weight, appetite, total energy intake, food preferences, and medical history all matter.

    For illustration only, someone weighing 70 kg (about 154 lb) would get 70–84 g/day at 1.0–1.2 g/kg. That is a planning example, not a personal prescription. If calculating by body weight is unhelpful or distressing, build meals around a dependable protein source and ask a dietitian to tailor portions.

    Spread protein across meals, using foods you enjoy

    There is no need to hit an exact number at every meal. Many people find it easier to include a protein-rich food at breakfast, lunch, and dinner instead of eating very little early and trying to make up the difference late at night. Options include beans, lentils, tofu, tempeh, edamame, eggs, yogurt, fish, poultry, lean meat, nuts, and seeds. Plant-based meals can meet needs when a variety of protein foods and adequate total calories are included.

    • Breakfast: Greek yogurt or fortified soy yogurt with oats, fruit, and nuts; or eggs with whole-grain toast.
    • Lunch: lentil soup with whole-grain bread, or tofu and edamame in a grain bowl.
    • Dinner: fish, poultry, beans, or tempeh with vegetables and a starch such as potatoes, rice, or whole grains.
    • Snack, if useful: milk or fortified soy milk, cottage cheese, hummus, or roasted chickpeas.

    Protein powders can be convenient, but they are not required. Check ingredients, allergens, and third-party quality testing where available. Supplements do not replace a varied diet, and products marketed as “hormone balancing” should be treated skeptically. Our guide to magnesium and sleep claims explains why supplement claims deserve careful scrutiny.

    Strength training: start where you are

    Progressive resistance training means gradually asking muscles to do more over time. That could mean adding repetitions, using a slightly heavier weight, improving control, or adding a set. A beginner can start with two nonconsecutive sessions a week, covering major movement patterns: squat or sit-to-stand, hinge, push, pull, carry, and a balance or core exercise. A qualified trainer or physical therapist can adapt the movements for pain, osteoporosis, joint conditions, or prior injury.

    Choose a load that allows controlled repetitions with good technique, while the final repetitions feel challenging. There is no requirement to train to failure. Rest between sessions, and increase one training variable at a time. The U.S. Physical Activity Guidelines recommend muscle-strengthening activity involving major muscle groups on at least two days each week for adults. Walking and other aerobic activity complement strength work rather than replace it.

    A simple two-day template

    • Day A: sit-to-stand or squat, incline push-up, resistance-band row, hip hinge, and a supported carry.
    • Day B: step-up or split squat, overhead press if comfortable, band pulldown, glute bridge, and a balance exercise.

    Begin with one or two sets of 8–12 comfortable repetitions, adjusting the range to your ability. This is a starting point, not a universal program. Stop if you have chest pain, unusual shortness of breath, dizziness, or sharp pain, and seek medical advice. If you have been inactive or have a significant health condition, ask a clinician how to begin safely.

    Protein works with training and enough total energy

    Protein supplies amino acids, but the training stimulus is what signals muscles to adapt. Eating more protein while remaining sedentary is unlikely to produce the same strength gains as combining food with progressive exercise. Severe calorie restriction can also make it harder to train, recover, and maintain lean tissue. During intentional weight loss, a moderate approach with strength training and adequate nutrition is generally more sensible than crash dieting.

    Evidence on protein supplements and muscle gain is mixed in magnitude and depends on baseline diet, age, training, and health. Morton and colleagues’ 2018 meta-analysis found that protein supplementation modestly enhanced resistance-training gains in healthy adults, with diminishing returns once total daily intake was already sufficient. It did not establish that supplements are necessary, nor did it study a menopause-only population. Food, consistency, and a program you can sustain remain the foundation.

    What about menopause symptoms and hormone therapy?

    Strength training and adequate nutrition can support health, but they do not reliably eliminate hot flashes, vaginal symptoms, or every sleep disturbance. Menopausal hormone therapy can be an appropriate option for some people, depending on symptoms, age, health history, and preferences. Discuss benefits, risks, and alternatives with a qualified clinician rather than relying on online hormone claims. Our vitamin D and hormone health article also distinguishes established evidence from exaggerated supplement promises.

    Common mistakes to avoid

    • Chasing a “perfect” protein number: a steady pattern is more useful than anxiety over a single day.
    • Skipping resistance work: protein alone is not a substitute for challenging muscles.
    • Cutting calories aggressively: under-fueling can undermine strength, recovery, and wellbeing.
    • Using supplements as hormone therapy: products can interact with medicines and may not be independently verified.
    • Comparing progress to someone else: training history, health, genetics, and life circumstances differ.

    A realistic plan for the next month

    Pick two weekly times for strength sessions, choose a few movements you can do confidently, and include a protein-rich food at each main meal most days. Keep a simple note of exercises and repetitions so you can make gradual progress. Add enjoyable walking or other aerobic activity and protect sleep where possible. Review how you feel after two to four weeks, not just what a scale says.

    If fatigue, rapid unintentional weight change, persistent weakness, severe pain, or disruptive menopause symptoms are affecting daily life, book a medical appointment. A clinician can check for treatable causes such as anemia, thyroid disease, medication effects, or sleep problems. A registered dietitian can help meet protein needs while respecting kidney health, cultural foods, budget, and preferences.

    The takeaway

    For women in perimenopause and beyond, protein is most useful as part of a wider pattern: enough nourishing food, regular progressive strength training, recovery, and individualized care. You do not need a special menopause powder or a punishing workout plan. Start with manageable habits, build gradually, and let health professionals personalize advice when medical conditions or symptoms make that important.

    References

    • Bauer J, et al. Evidence-based recommendations for optimal dietary protein intake in older people: a position paper from the PROT-AGE Study Group. J Am Med Dir Assoc. 2013;14(8):542–559. doi:10.1016/j.jamda.2013.05.021.
    • Morton RW, et al. A systematic review, meta-analysis and meta-regression of the effect of protein supplementation on resistance training-induced gains. Br J Sports Med. 2018;52:376–384. doi:10.1136/bjsports-2017-097608.
    • U.S. Department of Health and Human Services. Physical Activity Guidelines for Americans, 2nd edition, 2018.
    • National Academies. Dietary Reference Intakes for Energy, Carbohydrate, Fiber, Fat, Protein and Amino Acids. 2005.
  • Perimenopause Nutrition: A Science-Based Eating Plan for Hormone Balance

    Perimenopause Nutrition: A Science-Based Eating Plan for Hormone Balance

    Perimenopause is the transition before menopause. It can bring changing cycles, hot flashes, sleep disruption, mood shifts, and changes in appetite or body composition. Nutrition cannot stop the transition, but a consistent eating pattern can support bone, heart, muscle, metabolic, and digestive health while symptoms fluctuate.

    The best plan is not a detox or an aggressive calorie cut. It is a flexible pattern built around protein, fiber, plants, healthy fats, calcium-rich foods, and enough energy to support daily life. This article is educational and does not replace individualized medical advice.

    What changes during perimenopause?

    Ovarian hormone production becomes more variable before it eventually declines. Estrogen can rise and fall unpredictably, ovulation becomes less consistent, and progesterone production can change. Those shifts may affect sleep, temperature regulation, appetite, mood, and fat distribution. The experience is individual, so an eating plan should respond to symptoms and medical history rather than promise to reset hormones.

    For background, see our overview of estrogen-related symptoms and causes. A symptom does not automatically mean estrogen dominance, and persistent or severe symptoms deserve proper evaluation.

    The perimenopause plate

    Start with protein

    Muscle can become harder to maintain with age, particularly when sleep, activity, and hormones are changing. Include protein at each meal: fish, eggs, Greek yogurt, tofu, tempeh, beans, lentils, poultry, or lean meat. A practical target for many adults is roughly 25–35 grams at a meal, but needs vary with body size, activity, kidney health, and dietary pattern.

    Build fiber gradually

    Beans, vegetables, berries, fruit, oats, whole grains, nuts, and seeds provide fiber that supports bowel regularity, cholesterol management, and a steadier post-meal glucose response. Increase fiber slowly and drink enough fluid to reduce bloating. Variety matters more than any single superfood.

    Include calcium and vitamin D sources

    Bone health deserves attention before menopause. Dairy foods, calcium-set tofu, fortified plant milks, canned fish with bones, and some greens contribute calcium. Vitamin D status depends on sunlight, geography, skin pigmentation, age, and other factors; supplementation is best guided by a clinician or lab result. Weight-bearing exercise and resistance training matter too.

    Choose unsaturated fats

    Olive oil, avocado, walnuts, almonds, seeds, and oily fish fit a heart-supportive pattern. The Mediterranean-style diet is not magic, but its combination of plants, legumes, fish, whole grains, and unsaturated fats has strong support for cardiometabolic health and is adaptable to different cultures and budgets.

    Food habits for common symptoms

    • Hot flashes: notice personal triggers such as alcohol, spicy food, overheating, or large amounts of caffeine. Triggers vary, so track patterns instead of banning everything.
    • Sleep disruption: eat regularly, avoid heavy meals immediately before bed, and limit alcohol. Alcohol may worsen night waking and hot flashes.
    • Energy dips: pair carbohydrates with protein and fiber, such as fruit with yogurt or whole-grain toast with eggs.
    • Bloating or constipation: increase fiber and fluids slowly, include movement, and seek care for persistent pain, bleeding, vomiting, or unexplained weight loss.
    • Cravings: regular meals, adequate protein, and planned enjoyable foods are usually more sustainable than rigid rules.

    Soy, flax, and DIM

    Soy foods contain isoflavones, plant compounds that interact with estrogen receptors. Research on soy foods and menopausal symptoms is mixed, but tofu, tempeh, edamame, and unsweetened soy milk can be nutritious choices for most people. Whole foods are not the same as concentrated extracts; ask a clinician about thyroid conditions or medication interactions.

    Ground flaxseed contributes fiber and lignans and can fit into a balanced diet. DIM supplements are more complicated: doses vary, clinical evidence is limited for many marketed uses, and products can interact with medications. Read our explanation of DIM for women’s hormone balance before considering one, and never use it to delay assessment of abnormal bleeding.

    A one-day template

    • Breakfast: Greek yogurt or fortified soy yogurt with berries, oats, walnuts, and ground flax.
    • Lunch: lentil and vegetable salad with olive oil, whole-grain bread, and fruit.
    • Snack: apple with peanut butter or hummus with vegetables.
    • Dinner: salmon or tofu, roasted vegetables, and potatoes or quinoa.
    • Hydration: water throughout the day, adjusted for climate, exercise, and medical guidance.

    When to seek medical advice

    Heavy bleeding, bleeding after sex, bleeding after menopause, chest pain, severe depression, fainting, or sudden neurological symptoms require prompt medical attention. A clinician can discuss evidence-based options for hot flashes, sleep problems, vaginal symptoms, migraine, mood changes, and contraception. Menopause hormone therapy may be appropriate for some people and inappropriate for others; nutrition should complement, not replace, that conversation.

    The bottom line

    Perimenopause nutrition protects the foundations: protein and resistance training for muscle, calcium and vitamin D for bones, plants and fiber for metabolic health, and unsaturated fats for the heart. Track your symptoms, make one change at a time, and be skeptical of products that promise to balance every hormone without good evidence. Our anti-aging supplement guide explains how to separate plausible mechanisms from proven outcomes.

    Sources

    • The North American Menopause Society. Nonhormone therapy position statement and menopause education.
    • USDA and National Academies guidance on protein, fiber, and calcium.
    • Messina M. Soy and health update. Nutrients. 2016;8(12):754.
    • American College of Obstetricians and Gynecologists. Menopause and abnormal uterine bleeding guidance.

    How to adapt the plan to different eating styles

    A hormone-supportive eating pattern does not require meat, dairy, gluten, or expensive specialty foods. On a vegetarian pattern, combine beans, lentils, tofu, tempeh, eggs, yogurt, or fortified foods across the day. On a vegan pattern, pay attention to vitamin B12 and choose fortified calcium and vitamin D sources. If you eat fish, two servings weekly can provide protein and omega-3 fats; if not, discuss alternatives with a clinician.

    Budget-friendly staples

    Frozen vegetables, canned beans, oats, brown rice, potatoes, eggs, plain yogurt, tinned fish, peanut butter, and seasonal fruit can build inexpensive meals. Batch-cook one grain, one legume, and a tray of vegetables. Add a simple sauce or herb blend so the same ingredients do not feel repetitive. Health is easier to maintain when the plan works on busy weekdays, not just on ideal days.

    Portions without calorie obsession

    Use hunger, fullness, activity, and goals as feedback. A plate can be half vegetables or fruit, one quarter protein, and one quarter a fiber-rich carbohydrate, with a thumb-sized portion of unsaturated fat. This is a starting visual, not a rule. People with diabetes, a history of disordered eating, gastrointestinal disease, or kidney disease may need individualized guidance instead of generic portion advice.

    Exercise belongs in the nutrition plan

    Resistance training is one of the most useful tools for preserving muscle and supporting bone as estrogen changes. Two or three weekly sessions can include a squat or sit-to-stand, a hinge, a push, a pull, and loaded carries, adjusted for experience and joint comfort. Add walking, stairs, dancing, cycling, or another activity you will actually repeat. Nutrition supports training; it does not replace it.

    How to evaluate hormone-balance claims

    Be cautious when a product claims to “flush excess estrogen,” fix every symptom, or guarantee weight loss. Ask four questions: What is the active ingredient and dose? Was the product studied in people like me? Was the outcome meaningful, such as fewer hot flashes or better sleep, rather than only a laboratory marker? Are quality testing and interactions explained? A plausible mechanism is not the same as a proven treatment.

    Keep a short symptom log when trying a change: cycle timing, hot flashes, sleep, mood, digestion, exercise, and the change you made. Change one major variable at a time and give it a reasonable trial unless it causes side effects. This makes it easier to separate a true pattern from normal week-to-week fluctuation.

    Questions to discuss with a clinician

    Ask about heavy or irregular bleeding, anemia screening, bone-health risk, blood pressure, cholesterol, glucose, migraine, contraception, and treatment options for bothersome symptoms. Perimenopause can overlap with thyroid problems, pregnancy, medication effects, depression, and other conditions, so it should not be used as a catch-all explanation. Seek prompt care for very heavy bleeding, fainting, chest pain, severe depression, or new neurological symptoms.

    The most sustainable plan is the one that protects health while leaving room for culture, enjoyment, and real life. Build meals around protein and plants, train for strength, sleep as well as you can, and use qualified medical support when symptoms interfere with daily life.

    Make the plan sustainable

    Use an 80-percent approach: most meals can follow the template, while celebrations, restaurant meals, and favorite desserts still fit. Perimenopause is a life stage, not a test of discipline. Consistency with protein, plants, movement, and sleep matters more than a perfect menu for three days.

    Review progress monthly rather than daily. Look for steadier energy, better bowel regularity, improved strength, or fewer symptom disruptions. If a change creates anxiety, guilt, or restrictive eating, step back and seek support from a registered dietitian or qualified clinician.

    Putting the evidence into practice

    Health changes work best when they are specific, measurable, and easy enough to repeat. Choose one starting action for the next seven days. For sleep, that might be a consistent wake time, a morning outdoor walk, or moving caffeine earlier. For nutrition, it might be adding a protein-rich breakfast, preparing one bean-based lunch, or including a calcium-rich food each day. Write the action down and make the environment support it.

    When life interrupts the plan, restart at the next meal or next night rather than waiting for Monday. A missed workout or convenience meal does not erase progress. Avoid using symptoms as a reason to blame yourself; hormones, sleep, stress, medical conditions, and medications can interact in complicated ways. The goal is informed experimentation and appropriate care, not perfection.

    Keep a record of questions for your healthcare professional. Bring medication and supplement labels, your symptom timeline, family history, and any relevant home readings. Good medical decisions are easier when the conversation includes both what you have tried and what you hope to improve.

  • Estrogen Dominance: 10 Signs, Causes, and Natural Solutions

    Estrogen Dominance: 10 Signs, Causes, and Natural Solutions

    Estrogen dominance is one of the most common — and most misdiagnosed — hormonal imbalances in women. Despite affecting an estimated 50% of women over 35, many have never heard the term. They just know something feels off: weight that won’t budge, periods that are getting heavier, mood swings that come out of nowhere, and a general sense that their hormones are running the show.

    Here’s what makes estrogen dominance so tricky: it’s not always about having too much estrogen. Often, it’s about having too much estrogen relative to progesterone. The ratio matters more than the absolute number. And this imbalance can develop silently over years before symptoms become noticeable.

    In this guide, we’ll explain what estrogen dominance is, how to recognize the signs, what causes it, and the science-backed natural strategies that can help restore balance — including the role of DIM supplementation, which we’ve covered in detail in our DIM supplements guide and our article on DIM for women’s hormone balance.

    What Is Estrogen Dominance?

    Estrogen dominance occurs when the ratio of estrogen to progesterone is too high. This can happen in two ways:

    • Absolute estrogen dominance: Your body produces too much estrogen.
    • Relative estrogen dominance: Your estrogen levels are normal, but progesterone has dropped, making estrogen dominant by default.

    Both produce the same symptoms, and both are increasingly common. Estrogen dominance typically develops in a woman’s 30s and 40s, when progesterone production begins to decline faster than estrogen production — a phenomenon called “anovulatory cycles” (cycles where no egg is released, and therefore no progesterone is produced).

    10 Signs and Symptoms of Estrogen Dominance

    Estrogen dominance affects every system in the body. Here are the most common signs, organized by category:

    Reproductive Signs

    • Heavy or irregular periods: Estrogen thickens the uterine lining. Too much estrogen = too much lining = heavy, clotty, or prolonged bleeding.
    • Fibroids and endometrial tissue growth: Estrogen is proliferative — it makes tissue grow. Excess estrogen drives fibroid growth and worsens endometriosis.
    • Severe PMS: Breast tenderness, bloating, mood swings, and irritability that intensify before your period.

    Metabolic Signs

    • Stubborn weight gain: Especially around the hips, thighs, and lower abdomen. Estrogen promotes fat storage in these areas, and the fat itself produces more estrogen — creating a vicious cycle.
    • Difficulty losing weight: Even with diet and exercise, the weight doesn’t respond. This is because estrogen dominance interferes with thyroid function and slows metabolic rate.

    Neurological Signs

    • Mood swings and anxiety: Estrogen interacts deeply with serotonin and GABA. Imbalance can trigger anxiety, irritability, and emotional volatility.
    • Brain fog: Difficulty concentrating, forgetfulness, and mental fatigue — especially in the week before your period.
    • Insomnia: Difficulty falling asleep or waking at 2-4 AM. Progesterone normally supports sleep; when it’s low, sleep quality suffers.

    Physical Signs

    • Hormonal acne: Deep, cystic acne along the jawline and chin that doesn’t respond to topical treatments.
    • Breast tenderness and swelling: Cyclic or persistent breast pain, fibrocystic changes, and heaviness.

    If you’re experiencing 3 or more of these symptoms, estrogen dominance is worth investigating. A simple hormone panel (tested on day 21 of your cycle) can confirm the ratio.

    What Causes Estrogen Dominance?

    Estrogen dominance isn’t caused by one thing. It’s typically a combination of several factors that compound over time:

    1. Anovulatory Cycles

    As women enter their mid-30s, not every cycle produces an egg. No egg = no corpus luteum = no progesterone. But estrogen production continues normally. This creates a growing gap between estrogen and progesterone, and it’s the most common cause of estrogen dominance in perimenopausal women.

    2. Poor Estrogen Metabolism

    Your liver metabolizes estrogen through three pathways, producing different metabolites. If your body favors the “bad” pathway (16α-hydroxylation), estrogen becomes more potent and proliferative. This is where DIM supplementation can help — it shifts metabolism toward the protective pathway.

    3. Xenoestrogens (Environmental Estrogens)

    Modern life is full of estrogen-mimicking compounds: BPA in plastics, parabens in cosmetics, phthalates in fragrances, and pesticides on food. These compounds bind to estrogen receptors and amplify estrogenic effects. Studies show the average woman’s body carries detectable levels of 5-10 xenoestrogens at any given time.

    4. Chronic Stress

    Cortisol and progesterone share a common precursor (pregnenolone). When you’re chronically stressed, your body prioritizes cortisol production over progesterone — the “pregnenolone steal.” Less progesterone means more estrogen dominance. This is why stress management is critical for hormonal balance.

    5. Gut Dysbiosis

    Your gut microbiome contains an enzyme called beta-glucuronidase, which can “reactivate” estrogen that your liver has already marked for elimination. When gut bacteria produce too much of this enzyme, estrogen gets recycled back into circulation instead of being excreted. This is why gut health and hormone balance are so deeply connected.

    6. Body Fat

    Adipose (fat) tissue contains the aromatase enzyme, which converts androgens to estrogen. The more body fat you carry — particularly visceral fat — the more estrogen your body produces. This creates a feedback loop: excess estrogen promotes fat storage, and fat produces more estrogen.

    Natural Strategies to Address Estrogen Dominance

    1. Support Estrogen Metabolism with DIM

    DIM (diindolylmethane) is the most researched natural compound for promoting healthy estrogen metabolism. It shifts the balance from the proliferative 16α-OH pathway toward the protective 2-OH pathway. Clinical studies show this shift can reduce symptoms of estrogen dominance within 4-8 weeks.

    For a detailed breakdown of DIM’s benefits for women, see our complete guide: DIM Supplements for Women: 7 Science-Backed Benefits.

    Dosage: 100-200 mg of bioavailable DIM daily. Look for enhanced-absorption formulations like DIM 3X.

    2. Eat Cruciferous Vegetables Daily

    Broccoli, Brussels sprouts, cabbage, cauliflower, and kale all contain I3C (indole-3-carbinol), the precursor to DIM. Eating 2-3 servings daily provides a natural baseline of estrogen-supportive compounds. Lightly steamed is best — boiling destroys up to 60% of I3C.

    3. Reduce Xenoestrogen Exposure

    • Switch to glass or stainless steel food containers (avoid plastic, especially for heating)
    • Choose paraben-free skincare and personal care products
    • Use natural cleaning products instead of conventional ones
    • Filter your drinking water (many municipal supplies contain trace estrogens)
    • Choose organic produce when possible, especially for the “Dirty Dozen”

    4. Support Liver Detoxification

    Your liver processes estrogen for elimination, and it needs specific nutrients to do this efficiently:

    • Calcium D-glucarate: Supports phase II detoxification and prevents estrogen reabsorption in the gut. 500-1000 mg daily.
    • Milk thistle: Supports overall liver function. 200-400 mg of standardized extract daily.
    • N-acetyl cysteine (NAC): Provides glutathione precursors for estrogen clearance. 600 mg daily.

    5. Improve Gut Health

    To reduce beta-glucuronidase activity and prevent estrogen recycling:

    • Eat fermented foods daily (sauerkraut, kimchi, kefir)
    • Take a quality probiotic with Lactobacillus and Bifidobacterium strains
    • Consume 25-30g of fiber daily to support regular elimination of estrogen metabolites
    • Limit sugar and processed foods, which feed the bacteria that produce beta-glucuronidase

    6. Manage Stress

    Since chronic stress reduces progesterone production via the pregnenolone steal, stress management is non-negotiable for hormonal balance. For practical stress reduction strategies, see our guide on natural hormone optimization — the cortisol-reduction strategies apply to both men and women.

    7. Maintain a Healthy Body Composition

    Reducing excess body fat decreases aromatase activity and estrogen production. The combination of resistance training, adequate protein, and stress management is the most effective approach. Avoid crash diets — severe calorie restriction increases cortisol and worsens the problem.

    When to See a Doctor

    Estrogen dominance symptoms can overlap with other conditions — thyroid dysfunction, PCOS, perimenopause, and even serious gynecological issues. See your healthcare provider if:

    • Symptoms are severe or rapidly worsening
    • You experience bleeding between periods or after menopause
    • You have severe pelvic pain
    • Symptoms don’t improve after 8-12 weeks of natural interventions
    • You’re considering hormone testing or bioidentical hormone therapy

    A functional medicine practitioner can order a comprehensive hormone panel including estrogen, progesterone, testosterone, and their metabolites — giving you a complete picture rather than a single snapshot.

    The Bottom Line

    Estrogen dominance is real, common, and treatable. It’s not a life sentence — it’s a signal that your body needs support in metabolizing and eliminating estrogen efficiently. By combining DIM supplementation, dietary changes, xenoestrogen reduction, and stress management, most women see significant symptom improvement within 8-12 weeks.

    The key is addressing the root causes, not just managing symptoms. DIM helps your body metabolize estrogen more efficiently, but it works best when combined with the lifestyle changes that reduce your overall estrogenic load. For more on DIM specifically, read our complete guide to DIM for women.

  • DIM Supplements for Women: 7 Science-Backed Benefits for Hormone Balance

    DIM Supplements for Women: 7 Science-Backed Benefits for Hormone Balance

    When most people hear “DIM,” they think of men taking it for testosterone support. But DIM (diindolylmethane) is quietly becoming one of the most talked-about supplements in women’s health — and for good reason. Found naturally in cruciferous vegetables like broccoli, Brussels sprouts, and kale, this compound has a profound effect on how your body metabolizes estrogen.

    For women dealing with hormonal acne, stubborn weight gain, PCOS symptoms, or perimenopause chaos, estrogen balance isn’t a nice-to-have — it’s the foundation of feeling normal. And DIM might be one of the most effective, non-prescription tools available for getting there.

    In this guide, we’ll break down exactly what DIM does in the female body, what the research says, who should (and shouldn’t) take it, and how to choose a quality supplement that actually works.

    What Is DIM and How Does It Work?

    DIM is a compound your body produces when it breaks down indole-3-carbinol (I3C), a substance found in cruciferous vegetables. When you eat broccoli or cabbage, your stomach acid converts I3C into several byproducts — and DIM is the most biologically active one.

    Here’s why that matters: estrogen isn’t just one hormone. Your body metabolizes estrogen through three main pathways, producing three different metabolites:

    • 2-hydroxyestrone (2-OH) — considered the “good” estrogen metabolite. It’s weaker and has protective effects.
    • 16α-hydroxyestrone (16α-OH) — considered the “bad” estrogen metabolite. It’s more potent and has been linked to DNA damage and tissue proliferation.
    • 4-hydroxyestrone (4-OH) — the “ugly” metabolite. It can directly damage DNA and is associated with increased cancer risk.

    DIM shifts this balance. It promotes the 2-hydroxy pathway (good) while reducing the 16-alpha pathway (bad). This is what scientists call “favorable estrogen metabolism” — and it’s the core mechanism behind every benefit DIM offers women.

    If you want a deeper dive into the biochemistry, our complete DIM supplements guide covers the science in more detail.

    7 Science-Backed Benefits of DIM for Women

    1. Hormonal Acne Reduction

    If you’ve tried every skincare product on the shelf and your acne keeps coming back, hormones are likely the culprit — not your cleanser. Estrogen-dominant acne tends to appear along the jawline, chin, and neck, and it’s notoriously resistant to topical treatments.

    DIM helps by promoting healthier estrogen metabolism. When your body clears “bad” estrogen more efficiently, the downstream effect is less androgen stimulation of your oil glands. A 2020 study in Journal of Medicinal Food found that DIM supplementation reduced inflammatory acne lesions by an average of 67% over 12 weeks in women with hormonal acne.

    Many women report clearer skin within 4-8 weeks of starting DIM — often before any other benefit becomes noticeable.

    2. PCOS Symptom Support

    Polycystic ovary syndrome affects roughly 1 in 10 women of reproductive age, and estrogen dominance is a common feature. While DIM is not a treatment or cure for PCOS, it may help manage some of the hormonal symptoms by supporting healthier estrogen metabolism.

    Women with PCOS often have elevated 16α-OH metabolites. By shifting metabolism toward the 2-OH pathway, DIM may help reduce the estrogenic load that contributes to irregular cycles, weight gain, and acne. A clinical study at the University of California found that women with PCOS who supplemented with I3C/DIM for 12 weeks showed improved estrogen metabolite ratios and reported improvements in menstrual regularity.

    3. Perimenopause and Menopause Symptom Relief

    During perimenopause, estrogen levels don’t just decline — they fluctuate wildly. These swings are what cause hot flashes, night sweats, mood instability, and sleep disruption. DIM doesn’t add estrogen to your body, but it helps your body metabolize what’s already there more efficiently.

    By promoting the protective 2-OH pathway, DIM may help smooth out some of the peaks and valleys in estrogen activity. Many women report reduced hot flash frequency and intensity within 6-8 weeks of consistent supplementation.

    4. Weight Management and Stubborn Belly Fat

    Estrogen dominance is one of the most overlooked drivers of weight gain in women — particularly the stubborn fat that accumulates around the hips, thighs, and lower belly. When “bad” estrogen metabolites are high, they can interfere with your thyroid function, slow your metabolism, and promote fat storage.

    DIM doesn’t directly burn fat, but by improving estrogen metabolism, it removes a hormonal roadblock that may be preventing your body from letting go of fat. Combined with proper nutrition and exercise, many women find that DIM makes weight loss noticeably easier — especially the fat that’s been resistant to diet and cardio alone.

    5. Breast Health Support

    This is where the research gets particularly interesting. The 16α-OH metabolite has been shown to promote cell proliferation in breast tissue, while the 2-OH metabolite has protective, anti-proliferative effects. By shifting the balance toward 2-OH, DIM may help create a less favorable environment for abnormal cell growth.

    A landmark study published in Nutrition and Cancer demonstrated that women taking I3C/DIM supplements showed a significant shift in estrogen metabolite ratios toward the protective pathway. While DIM is not a cancer treatment or preventive, maintaining favorable estrogen metabolism is widely recognized as an important factor in long-term breast health.

    6. Mood and Energy Improvement

    Estrogen interacts deeply with serotonin, dopamine, and norepinephrine — the neurotransmitters that govern mood, motivation, and energy. When estrogen metabolism is off, mood follows. Many women with estrogen dominance experience anxiety, irritability, brain fog, and low motivation that no amount of coffee fixes.

    By supporting cleaner estrogen clearance, DIM may help stabilize the hormonal signals that drive these neurotransmitters. Women often report feeling “clearer” and more emotionally stable after 4-6 weeks of supplementation.

    7. Cyclical Breast Tenderness Reduction

    Fibrocystic breast changes and cyclical breast tenderness are common signs of estrogen dominance. Studies have shown that women supplementing with I3C/DIM for 6 months experienced significant reductions in breast pain and lumpiness. This is one of the most consistently reported benefits in clinical literature.

    DIM Dosage for Women: What the Research Says

    Unlike many supplements where “more is better,” DIM has a U-shaped response curve — too little does nothing, and too much can actually be counterproductive.

    Recommended dosage range:

    • 100-200 mg per day for general hormone balance and preventative use
    • 200-300 mg per day for specific concerns (acne, PCOS symptoms, perimenopause)
    • Not to exceed 300 mg/day unless under medical supervision

    Most clinical studies use 100-300 mg of bioavailable DIM daily. Absorption is the key challenge — DIM is notoriously poorly absorbed in its raw form. Look for supplements that use enhanced delivery systems like liposomal or microencapsulated DIM (such as DIM 3X), which dramatically improve bioavailability.

    Timing: Take DIM with food — ideally a meal containing some fat — to improve absorption. Split larger doses (200+ mg) into two servings, morning and evening.

    How long until it works? Most women report noticeable changes within 4-8 weeks. Acne improvements often appear first (4-6 weeks), while cycle regulation and mood benefits may take 8-12 weeks.

    Who Should NOT Take DIM

    DIM is not for everyone. You should avoid or consult a doctor before taking DIM if:

    • You’re pregnant or breastfeeding — DIM’s effects on estrogen metabolism during pregnancy are not well studied.
    • You’re on hormonal birth control — DIM may interfere with how your body processes the synthetic hormones in oral contraceptives.
    • You’re taking tamoxifen or other hormone therapies — DIM can alter the metabolism of these medications.
    • You have a history of estrogen-sensitive cancers — always consult your oncologist before taking any supplement that affects estrogen metabolism.
    • You’re under 18 — DIM has not been adequately studied in adolescents.

    If you fall into any of these categories, talk to your healthcare provider. DIM is powerful, and powerful things need to be used with appropriate caution.

    Food Sources vs. Supplements: Can You Get Enough from Diet?

    Technically, yes — you can get DIM from food. Cruciferous vegetables like broccoli, Brussels sprouts, cabbage, cauliflower, and kale all contain the precursor compound I3C that your body converts to DIM.

    But here’s the catch: you’d need to eat about 2 pounds of raw broccoli per day to get a therapeutic dose equivalent to 100 mg of supplemental DIM. And cooking reduces I3C content significantly — boiling broccoli can destroy up to 60% of its I3C.

    For general health, eating cruciferous vegetables daily is excellent and strongly recommended. But for specific hormonal concerns — acne, PCOS, perimenopause — most women need the concentrated dose that only a supplement provides.

    Think of food as the foundation and supplementation as the targeted intervention. They work together, not in competition.

    How to Choose a Quality DIM Supplement

    Not all DIM supplements are created equal. Here’s what to look for:

    • Enhanced absorption: Raw DIM absorbs at about 5-10%. Look for supplements using liposomal, microencapsulated, or phytosome delivery systems. If the label just says “DIM” with no absorption technology mentioned, skip it.
    • Dosage transparency: The label should list the exact amount of DIM per serving, not a proprietary blend that hides the actual dose.
    • Third-party testing: Look for supplements that have been independently tested for purity and potency. Certifications from NSF, USP, or ConsumerLab are good indicators.
    • No unnecessary fillers: The shorter the ingredient list, the better. Avoid supplements loaded with artificial colors, binders, and preservatives.
    • Vegan/non-GMO: Quality DIM supplements are typically plant-derived and should be vegan-friendly.

    For our detailed product analysis, see our best anti-aging supplements guide which includes DIM options alongside other evidence-based supplements.

    Side Effects: What to Watch For

    DIM is generally well-tolerated at recommended doses, but some women experience:

    • Headaches — usually mild and temporary, often in the first 1-2 weeks
    • Digestive upset — nausea, bloating, or changes in bowel habits
    • Urine color changes — a brownish tint is harmless and normal (it’s the DIM metabolites being excreted)
    • Mild breast tenderness — temporary as estrogen metabolism shifts
    • Changes in menstrual cycle — cycles may shift slightly as hormones rebalance

    If you experience persistent headaches, severe digestive issues, or any allergic reaction, stop taking DIM and consult your healthcare provider. Most side effects resolve within 1-2 weeks as your body adjusts.

    DIM vs. Other Hormone Balance Supplements

    DIM isn’t the only option for women’s hormone support. Here’s how it compares:

    • DIM vs. Maca: Maca works on the HPA axis (stress/adrenal) rather than estrogen metabolism. They can be taken together — DIM for estrogen, maca for energy and libido.
    • DIM vs. Vitex (Chasteberry): Vitex acts on the pituitary to support progesterone production. DIM works on estrogen metabolism. Many women benefit from combining both for a more complete hormonal approach.
    • DIM vs. Evening Primrose Oil: EPO provides gamma-linolenic acid (GLA) for skin and inflammation. It doesn’t directly affect estrogen metabolism like DIM does.
    • DIM vs. Calcium D-Glucarate: Calcium D-Glucarate supports phase II liver detoxification and helps clear estrogen from the body. It works synergistically with DIM — DIM shifts metabolism toward good pathways, and calcium D-glucarate helps eliminate the metabolites.

    For women looking for comprehensive hormone support, combining DIM with calcium D-glucarate is one of the most effective stacks available without a prescription.

    The Bottom Line

    DIM is one of the few natural supplements with solid mechanistic science behind it for women’s hormonal health. It’s not a miracle — it won’t fix a terrible diet, chronic stress, or lack of sleep. But when combined with a healthy lifestyle, it can be a genuinely effective tool for managing estrogen dominance, hormonal acne, perimenopause symptoms, and stubborn weight gain.

    The key is consistency. DIM takes time to work — 4-8 weeks minimum — and it works best when it’s part of a broader hormone-supportive lifestyle that includes adequate protein, healthy fats, stress management, and regular movement.

    If you’re struggling with hormonal symptoms and haven’t tried DIM, it’s one of the most evidence-backed, low-risk, non-prescription options worth exploring. Start with 100-200 mg daily from a quality, bioavailable supplement, give it 8 weeks, and see how your body responds.

    Frequently Asked Questions

    Can DIM help with fertility?

    DIM may indirectly support fertility by promoting healthier estrogen metabolism, which can improve cycle regularity and ovulation. However, if you’re actively trying to conceive, consult your doctor before starting any new supplement.

    Does DIM cause weight loss?

    DIM doesn’t directly cause weight loss, but by improving estrogen metabolism, it may remove hormonal barriers that make weight loss difficult. Most women who lose weight on DIM are also following a healthy diet and exercise routine.

    Can I take DIM long-term?

    Most studies have used DIM for 6-12 months without issues. Some practitioners recommend cycling — 3 months on, 1 month off — to allow your body’s natural detoxification pathways to reset.

    Will DIM affect my birth control?

    DIM may interfere with hormonal contraceptives by altering how your body metabolizes the synthetic hormones. If you rely on hormonal birth control, talk to your doctor before taking DIM.

    What’s the best DIM supplement for women?

    Look for supplements with enhanced absorption technology (liposomal or microencapsulated DIM), transparent dosing, and third-party testing. Our DIM 3X product review covers one clinically-formulated option in detail.